
1. Pathophysiology of Right Ventricular Air Lock
Venous Air Embolism (VAE) occurs when atmospheric air is drawn into the venous circulation through an un-clamped catheter lumen, disconnected hub, or open subcutaneous tract. Under normal spontaneous respiration, intrathoracic pressure drops to -2 to -5 cm H2O during inhalation; in an upright patient, this creates a negative pressure gradient capable of entraining 100 mL of air per second through a 14-gauge catheter.
When air reaches the heart, it churns with blood in the right ventricle, creating a foamy 'air lock' across the pulmonary valve outflow tract. This blocks blood flow into the pulmonary arteries, precipitating acute right-sided heart failure (cor pulmonale), severe ventilation-perfusion mismatch, systemic hypoxemia, and sudden cardiac arrest. In the 25% to 30% of patients with a patent foramen ovale (PFO), venous air can cross into the left atrium, causing paradoxical arterial stroke or myocardial infarction.
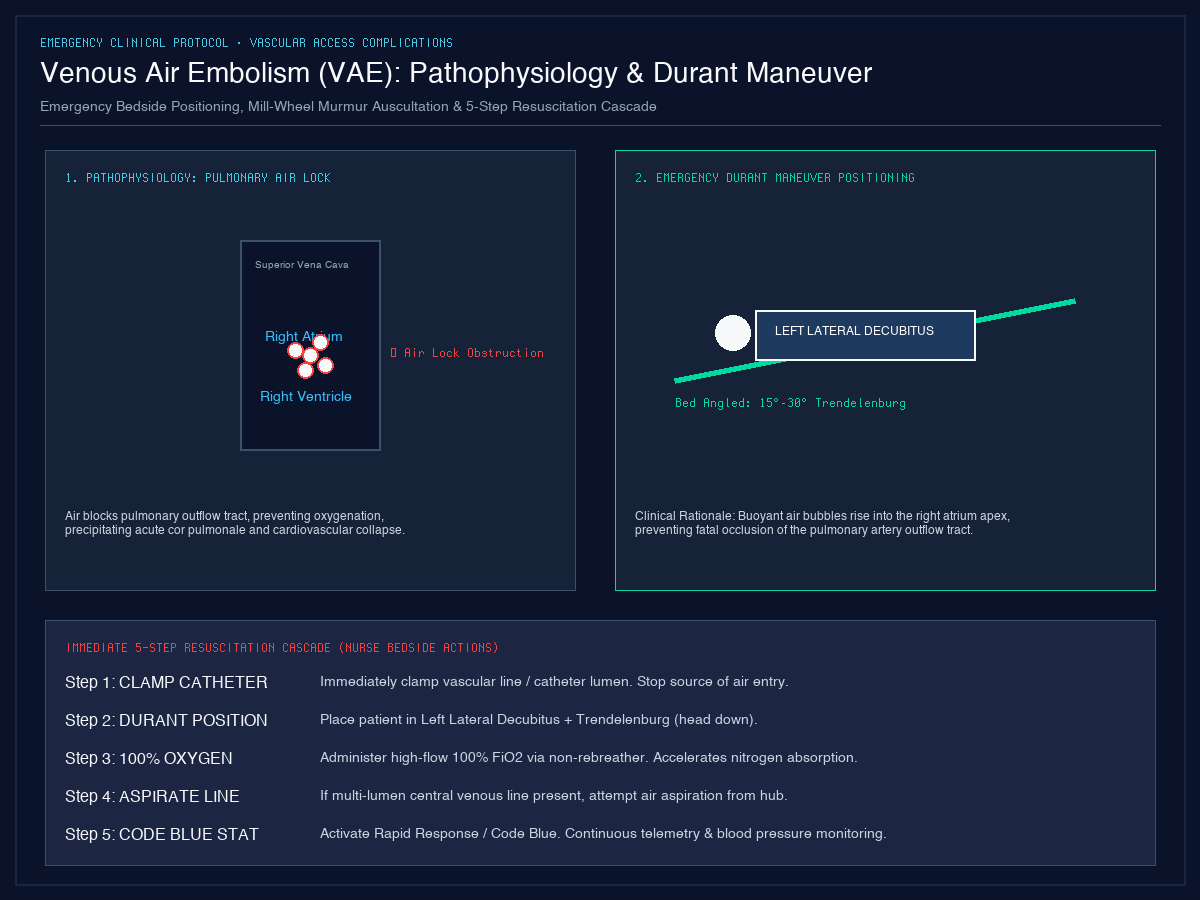
2. Emergency Durant's Maneuver & 5-Step Resuscitation Cascade
3. Catheter Removal Technique & Engineering Controls
Up to 30% of venous air embolisms occur during catheter removal when atmospheric air enters the subcutaneous tract before fibrin sealing occurs. Safe removal mandates:
- Position patient supine or in slight Trendelenburg position (never upright or sitting).
- Instruct patient to perform a Valsalva maneuver (bear down) or exhale during catheter withdrawal to ensure positive intrathoracic pressure.
- Immediately cover insertion tract with sterile petroleum gauze and an airtight occlusive dressing, maintained intact for at least 24 hours.
- Use infusion sets equipped with air-eliminating 0.2 µm hydrophobic filters and AirStop hydrophilic membranes that automatically stop fluid flow when dry.